

Short-term ibuprofen at the lowest effective dose is an effective and usually safe first-line option for menstrual cramps for most people, but it carries specific gastrointestinal, cardiovascular, renal, and allergic risks you need to know. Most people only notice mild stomach upset or dizziness. Rarer but serious risks include GI bleeding, heart events, and kidney injury. Stop taking it and seek emergency care if you vomit blood, pass black stools, or feel chest pain, sudden weakness, slurred speech, trouble breathing, or a severe allergic reaction.
TL;DR:
- Most users experience only mild, temporary side effects like stomach upset or dizziness, which typically resolve within a few days.
- Serious risks such as gastrointestinal bleeding, cardiovascular events, or kidney injury mainly affect those with pre-existing conditions or who take higher or prolonged doses.
- Ibuprofen’s pain-relief effectiveness depends on early use at the lowest effective dose, avoiding dosage escalation that increases side-effect risks.
- People with a history of ulcers, heart disease, or who are on blood thinners should consult a healthcare professional before taking ibuprofen.
- Non-drug therapies like heat, exercise, or wearable devices such as NuFemme can help reduce dependence on NSAIDs for menstrual cramps.
Table of Contents
- How ibuprofen relieves menstrual cramps
- Common, dose-related side effects you’re most likely to see
- Serious but rare adverse events and how to recognize them
- Dosing and practical safe-use rules for menstrual cramps
- Who should avoid ibuprofen and important drug interactions to check
- How to reduce side-effect risk and safer strategies for repeated need
- Evidence-backed drug-free options and how they fit into care
- Weighing relief against risk
- NuFemme: a drug-free way to ease cramps without the pill
- FAQ
- Sources
How ibuprofen relieves menstrual cramps
Period cramps happen because your uterus produces prostaglandins, hormone-like compounds that trigger muscle contractions to shed the uterine lining. When prostaglandin levels run high, those contractions get stronger and more painful, sometimes cutting off blood flow to the uterus briefly, which adds to the ache.
Ibuprofen works by blocking cyclooxygenase (COX) enzymes, which your body uses to make prostaglandins. Less prostaglandin production means calmer uterine contractions and less pain signaling, which is why ibuprofen tends to work better for cramps than a general pain reliever like acetaminophen.
This mechanism is also backed by solid comparative evidence. A network meta-analysis of OTC analgesics for dysmenorrhea ranked ibuprofen among the most effective options for primary dysmenorrhea, with a high probability of being among the top performers compared with other common over-the-counter choices. A separate Cochrane review of NSAIDs for dysmenorrhea found that NSAIDs as a class reduce pain and missed school or work days better than placebo, though they come with a higher chance of mild side effects than taking nothing at all.
Here is the catch built into the mechanism itself: the same COX inhibition that calms your uterus also reduces prostaglandins that protect your stomach lining. Prostaglandins help your stomach produce protective mucus and regulate acid, so when ibuprofen suppresses them everywhere in your body, not just your uterus, your stomach lining becomes more vulnerable. That is not a side effect unrelated to how the drug works. It is the direct tradeoff of the same chemical pathway that relieves your cramps, which is why gastrointestinal symptoms are the most common complaint among people taking ibuprofen for any reason, menstrual pain included.

Understanding this tradeoff matters for dosing. Because the pain relief and the GI risk come from the same mechanism, you cannot increase one without increasing the other. That is the core reason dosing guidance emphasizes the lowest dose that controls your pain rather than the maximum allowed.
Common, dose-related side effects you’re most likely to see
Most people who take ibuprofen for cramps experience, at most, mild and temporary discomfort. These symptoms tend to show up within the first few doses and usually fade once you stop taking the drug or your body adjusts.
- Stomach upset: nausea, heartburn, indigestion, or abdominal discomfort are the most frequently reported complaints.
- Digestive changes: diarrhea or constipation can occur, usually mild and short-lived.
- Dizziness or headache: some people notice lightheadedness or a dull headache, especially with higher doses.
- Skin reactions: mild rash or itching shows up occasionally and typically resolves after stopping the drug.
- Ringing in the ears: transient tinnitus has been reported in some users, particularly with repeated higher doses.
A PMC review of NSAID gastrointestinal risks found that a noticeable minority of people in clinical trials report gastrointestinal complaints while taking ibuprofen. That is a wide range, and it reflects differences in dose, duration, and individual sensitivity, but it tells you GI symptoms are common enough that you should expect some possibility of mild stomach discomfort, not treat it as unusual.
These symptoms generally start within the first one or two doses if they are going to appear at all, and they resolve within a day or two of stopping the medication. Taking ibuprofen with food, a full glass of water, or milk can blunt the stomach irritation without reducing how well it controls your pain. If nausea or indigestion persists beyond your typical three to five days of period pain, that is a signal to reassess rather than push through with higher doses.
Serious but rare adverse events and how to recognize them
The vast majority of people who take ibuprofen for a few days each month never experience anything beyond mild stomach upset. But the serious risks are worth understanding clearly, because they can escalate quickly and some have no early warning signs.
Gastrointestinal bleeding, ulcers, and perforation are the most well documented serious risk. They can develop without any preceding stomach pain, especially in people who use NSAIDs frequently, at higher doses, or alongside anticoagulants or corticosteroids. The longer and higher the dose, the greater the risk climbs.
Cardiovascular events, including heart attack, stroke, and heart failure, are a documented concern with NSAID use. The FDA drug label information warns that NSAIDs, including ibuprofen, increase the risk of serious cardiovascular events, especially at higher-than-recommended doses or with long-term use. This risk is far more relevant to someone taking ibuprofen daily for chronic pain than to someone using it for three to five days a month, but it is part of why “lowest effective dose, shortest duration” is not just a suggestion.
Kidney injury can occur because prostaglandins help regulate blood flow to the kidneys, and suppressing them can strain kidney function, particularly in people who are dehydrated or have existing kidney disease. Severe liver injury is rare but documented.
Severe allergic reactions and skin reactions, including anaphylaxis and rare but dangerous conditions like Stevens-Johnson syndrome, can develop even in people who have taken ibuprofen before without issue.
Call 911 or go to the emergency room immediately if you notice any of the following:
- Vomiting blood or material that looks like coffee grounds.
- Black, tarry, or bloody stools.
- Chest pain, pressure, or pain spreading to your arm or jaw.
- Sudden weakness, slurred speech, or facial drooping.
- Trouble breathing, swelling of the face or throat, or a widespread rash with blistering.
Dosing and practical safe-use rules for menstrual cramps
Getting the dose right is the single biggest lever you have over both pain relief and side-effect risk. Follow label directions as your baseline, and adjust only with a clinician’s input.
- Use the lowest dose that controls your pain, typically 200 to 400 milligrams every four to six hours as needed, and never exceed the maximum listed on the package label.
- Start dosing at the first sign of cramping or spotting rather than waiting for pain to peak. ACOG guidance recommends NSAIDs as a first-line option for painful periods and notes they work best when taken early, before prostaglandin levels and pain intensity build up.
- For severe cramps, some clinicians recommend a brief scheduled course rather than waiting for pain to hit before each dose. Discuss this approach with a clinician rather than self-scheduling an aggressive regimen.
- Never combine ibuprofen with another NSAID, including naproxen or aspirin used for pain, and check combination cold or flu products for hidden NSAID ingredients.
- Adolescents should use age-appropriate dosing per the package label or a pediatrician’s guidance, and those who are breastfeeding should check with a clinician, since ibuprofen is generally considered compatible with breastfeeding in short courses but individual circumstances vary.
- Contact a clinician if pain lasts more than ten days, if new symptoms appear, or if you notice any red-flag signs described above.
The through-line here is restraint: ibuprofen is meant to be a short, targeted tool for a predictable few days each month, not a standing daily medication.
Who should avoid ibuprofen and important drug interactions to check
Not everyone is a good candidate for ibuprofen, even for occasional period pain. Some conditions make it outright unsafe, while others simply raise the risk enough that you should talk to a clinician or pharmacist first.
- Avoid entirely if you have had a severe allergic reaction to ibuprofen or other NSAIDs in the past, or if you have had recent coronary artery bypass graft surgery.
- Use with caution if you have a history of peptic ulcers or GI bleeding, take anticoagulants, have advanced kidney disease, have uncontrolled high blood pressure, or have existing heart disease.
- Watch for interactions with blood thinners, since the combination raises bleeding risk substantially, according to FDA patient medication guidance, which flags concurrent anticoagulant, corticosteroid, or heavy alcohol use as factors that heighten GI bleed risk.
- SSRIs and SNRIs taken alongside ibuprofen can also raise bleeding risk, a combination worth flagging to your prescriber if you take an antidepressant regularly.
- Low-dose aspirin users should know that ibuprofen can interfere with aspirin’s heart-protective effect if timed incorrectly, so talk to a clinician about spacing the two if you take daily aspirin.
- Other considerations: MedlinePlus notes that people with asthma, bleeding disorders, liver disease, or kidney disease should check with a clinician before using ibuprofen.
If you take any regular prescription medication, a quick pharmacy medication review before starting a new OTC NSAID routine is a simple, free way to catch interactions before they become a problem.
How to reduce side-effect risk and safer strategies for repeated need
If you reach for ibuprofen every cycle, a few habits lower your risk without giving up the pain relief you count on. Take it with food or milk rather than on an empty stomach, keep alcohol intake light while you are dosing, and stick to the lowest dose that controls your pain for the shortest number of days you actually need it.
For people who need NSAIDs frequently, clinicians have additional protective strategies. Co-prescribing a proton pump inhibitor can reduce stomach acid and protect the lining during regular NSAID use, according to guidance from the Hospital for Special Surgery. Testing for and treating H. pylori infection, a bacteria linked to ulcer risk, is another option your clinician might raise. In some cases, switching to a COX-2 selective agent, which is gentler on the stomach lining, is worth discussing if standard ibuprofen repeatedly causes GI symptoms.
Lifestyle measures that reduce cramp severity can also lower how much ibuprofen you actually need each cycle, which indirectly reduces your exposure to side effects over time.
Pro Tip: Pair ibuprofen with a heating pad or wearable heat device during the first day of your period: reducing how hard your uterus has to work can mean needing fewer doses overall.

Evidence-backed drug-free options and how they fit into care
Non-drug approaches can meaningfully reduce period pain, and for some people they reduce or replace the need for ibuprofen altogether. Heat therapy has some of the most consistent evidence for short-term symptom relief, working by increasing blood flow and relaxing uterine muscle. Other options with varying evidence include TENS units, moderate exercise, magnesium supplementation, and relaxation techniques, each helpful for some people though none works as universally as NSAIDs for severe pain.
- Heat therapy relaxes cramping muscles and offers reliable short-term relief for many people.
- Movement and light exercise can ease cramp intensity for some, likely by improving circulation.
- Magnesium and relaxation techniques show promise in smaller studies, though evidence is less robust than for heat.
This is where a wearable like NuFemme fits into the picture as one option among these drug-free approaches. It combines heat, massage, and red-light (infrared) therapy in a cordless device worn under clothing, which means you are not tied to an outlet or stuck waiting at home for a heating pad to work. For people who want to minimize how often they reach for ibuprofen, pairing heat-based relief with an occasional short NSAID course on the heaviest days is a reasonable middle ground. For lighter cramps, non-drug methods alone may be enough.
Weighing relief against risk
Ibuprofen earns its place as a first-line option for period pain because the evidence behind it is solid and the risks, for most people using it a few days a month, are low. But “usually safe” is not the same as risk-free, and the people who get into trouble with NSAIDs are often the ones who never stopped to ask whether their personal risk factors, a blood thinner, a kidney condition, a history of ulcers, changed the calculation. Know your own risk profile before you treat ibuprofen as routine. If cramps keep you reaching for it every month without fail, that is worth a conversation with a clinician, not just a bigger bottle. And if you would rather skip the pill altogether on some cycles, drug-free options deserve a real look, not just a backup slot.
— Lavinia
NuFemme: a drug-free way to ease cramps without the pill
If you are looking to cut back on how often you reach for ibuprofen, or you just want a gentler first option before you consider medication at all, NuFemme is built around that exact need. It is a cordless wearable that combines heat, massage, and red-light therapy in one belt, worn discreetly under your clothes so you can keep working, running errands, or moving through your day instead of waiting at home for a heating pad.
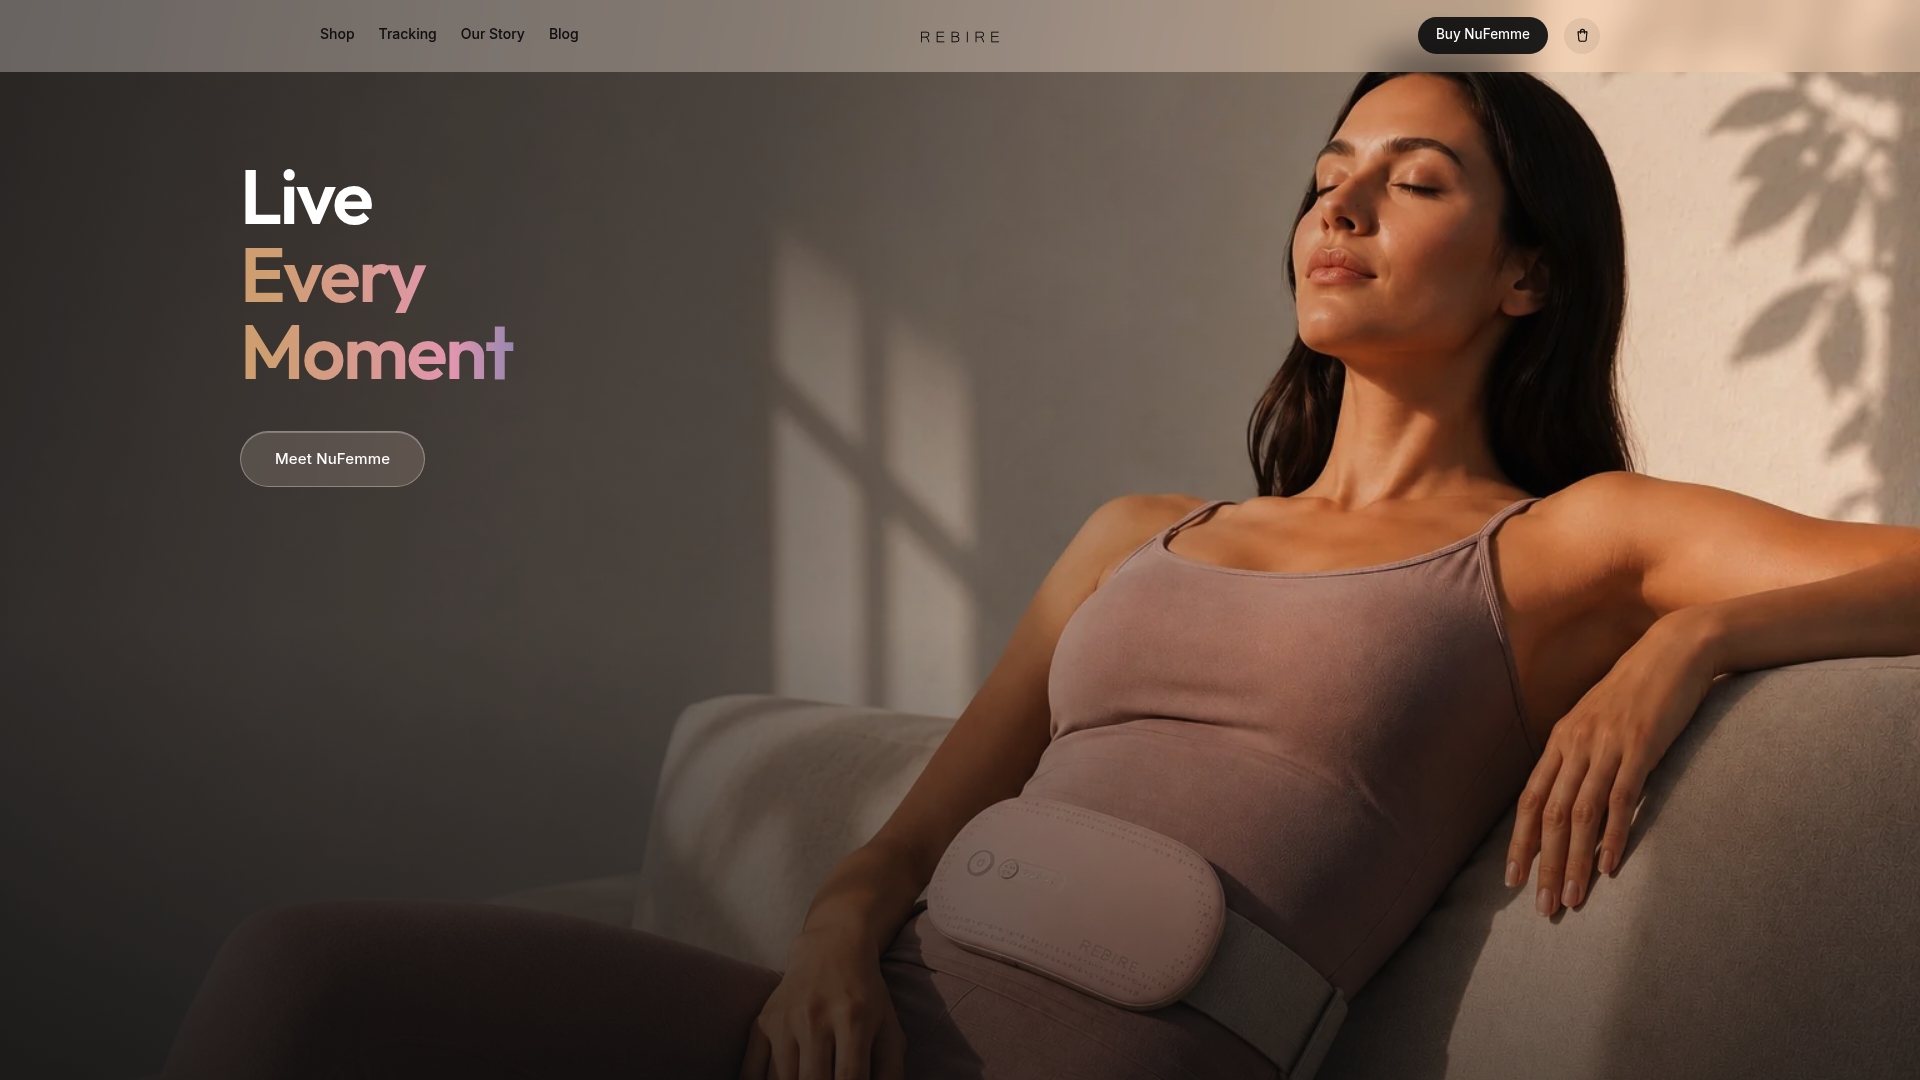
- Three heat levels and three massage speeds let you dial in what feels right for your body, whether you are at your desk or trying to wind down at night.
- A user-reported figure suggests that many users experience reduced pain within 15 minutes, though this is not from a clinical trial.
- It fits well for people who want an alternative on lighter cramp days, or who want to pair it with a short ibuprofen course on heavier ones.
If you have ever wanted a thoughtful way to support someone through their cycle, NuFemme also works well as a gift, the kind that says you have actually paid attention to what she deals with every month. Check out NuFemme for period cramps to see if it fits into how you manage your own relief.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
Why do doctors say not to take ibuprofen?
Doctors do not advise against ibuprofen broadly, but they caution against it for people with certain conditions, including a history of GI bleeding or ulcers, advanced kidney disease, uncontrolled heart disease, or an allergy to NSAIDs. The concern centers on cardiovascular, kidney, and gastrointestinal risks that rise with higher doses, longer use, or certain drug combinations, as outlined in FDA label warnings.
What are the top 3 side effects of ibuprofen?
The most commonly reported side effects are gastrointestinal symptoms like nausea, heartburn, and stomach pain, along with dizziness and headache. A PMC review found gastrointestinal complaints occur in 4% to 16% of people in clinical trials, making stomach-related symptoms the most frequent complaint by far.
What organ is most affected by ibuprofen?
The stomach lining is the organ most commonly affected, since ibuprofen reduces the protective prostaglandins that shield it from acid, which is why gastrointestinal symptoms are the most frequently reported issue. The kidneys and, more rarely, the liver can also be affected, particularly with higher doses or long-term use.
Is ibuprofen bad for cramps?
Ibuprofen is not bad for cramps. A network meta-analysis found it among the most effective OTC options for primary dysmenorrhea, and it is widely recommended as a first-line choice when used at the lowest effective dose for a short duration.
Sources
- Network meta-analysis (2020) of OTC analgesics for dysmenorrhea
- PMC review on NSAID gastrointestinal risks
- Dailymed / FDA drug information summary